Elevate Testosterone & Weight Loss

Healthcare provider explaining insurance coverage for weight loss treatment to a patient while reviewing documentation during a clinical consultation

Will Insurance Cover the Cost of Medical Weight Loss Treatment?

Will Insurance Cover the Cost of Medical Weight Loss Treatment? Table of Contents 1. Why This Question Stops So Many People From Starting 2. What Insurance Coverage for Weight Loss Actually Looks Like 3. How ACA Marketplace Plans Handle GLP-1 Coverage 4. Medicaid Coverage for Weight Loss Medications 5. What Employer-Sponsored Plans Typically Cover 6. What Patients Without Coverage Can Expect to Pay 7. Frequently Asked Questions 8. What to Do Before You Assume You Are Not Covered For many people considering medical weight loss treatment, the first practical question is not whether it will work. It is whether their insurance will pay for it. Insurance coverage for weight loss medications is one of the most confusing areas of health benefits, and the gap between what patients expect and what their plan covers can be significant. This blog explains how insurance coverage for weight loss treatment works across different plan types, what determines whether GLP-1 medications are covered, what prior authorization involves, and what options exist when plans do not cover these treatments. 1. Why This Question Stops So Many People From Starting The cost of GLP-1 medications without insurance can reach approximately one thousand dollars per month at list price. For most people, that figure makes insurance coverage an immediate practical concern. Coverage varies dramatically depending on the type of plan a patient has, what condition the medication is prescribed for, and which specific medication is used. A patient with employer-sponsored coverage may find their GLP-1 fully covered. A patient with an ACA Marketplace plan may find the same medication is not on their formulary at all. Understanding which category your coverage falls into is the first step toward knowing your options. Understanding clinical eligibility is equally important. The blog Who Is a Good Candidate for Medical Weight Loss Treatments? covers those clinical criteria in practical detail. 2. What Insurance Coverage for Weight Loss Actually Looks Like Insurance coverage for weight loss medications operates differently than coverage for most other prescription drugs. The key factor is how the condition being treated is classified by the plan. According to NIDDK, some but not all insurance plans cover medications that treat overweight and obesity, and patients should contact their insurance provider directly to confirm whether their specific plan covers these medications. Several factors determine whether a GLP-1 medication is covered: The diagnosis code on the prescription: obesity, prediabetes, type 2 diabetes, and cardiovascular disease each trigger different coverage rules Which specific medication is prescribed: Ozempic and Wegovy contain the same active ingredient but are treated very differently by most plans The patient’s BMI and any documented weight-related health conditions Whether the plan covers obesity as a standalone condition or requires a comorbidity such as hypertension or sleep apnea Whether prior authorization is required and whether the patient meets the plan’s approval criteria The same drug, at the same dose, for the same patient can be covered or denied based solely on which diagnosis is on the prescription and which plan the patient has. 3. How ACA Marketplace Plans Handle GLP-1 Coverage ACA Marketplace plans are the most restrictive for GLP-1 coverage. These are plans purchased through state or federal exchanges by individuals without employer-sponsored insurance. According to KFF, Wegovy is covered by just 1 percent of ACA Marketplace prescription drug plans, compared to 82 percent that cover Ozempic. Both contain the same active ingredient, semaglutide. Ozempic is approved for type 2 diabetes while Wegovy is approved for obesity, this single FDA indication difference produces an enormous gap in coverage rates. Key implications for ACA Marketplace plan holders include: A patient prescribed semaglutide for obesity is very unlikely to have it covered as Wegovy A patient with comorbid type 2 diabetes prescribed Ozempic may find it covered, with weight loss as a secondary benefit All ACA Marketplace plans that cover GLP-1 medications for obesity require prior authorization Plans frequently impose quantity limits and require documentation of prior weight loss attempts For patients whose GLP-1 prescriptions are denied, an appeal process exists. The appeal requires provider documentation establishing medical necessity, relevant lab results, and records of prior weight loss efforts. A meaningful percentage of initial denials are overturned on appeal. 4. Medicaid Coverage for Weight Loss Medications Medicaid coverage for GLP-1 medications operates under a distinct framework. Federal law requires state Medicaid programs to cover nearly all FDA-approved drugs, but weight loss medications are specifically excluded from this requirement. According to KFF, only 13 state Medicaid programs cover GLP-1s for obesity treatment under fee-for-service as of January 2026. Coverage for type 2 diabetes, cardiovascular disease, and sleep apnea is required, so a patient prescribed Ozempic for diabetes would have it covered while the same patient prescribed Wegovy for obesity might not. The Medicaid landscape is evolving. In late 2025, the Trump administration announced agreements with Novo Nordisk and Eli Lilly to reduce GLP-1 prices for Medicaid enrollees. A new five-year CMMI model called BALANCE was introduced in December 2025 to expand access through negotiated pricing and standardized coverage criteria. Patients on Medicaid should: Contact their state Medicaid office to confirm whether GLP-1s for obesity are covered Ask whether their diagnosis qualifies for required coverage under diabetes, cardiovascular disease, or sleep apnea indications Ask their provider whether the medication can be prescribed under a covered indication if clinically appropriate 5. What Employer-Sponsored Plans Typically Cover Understanding insurance coverage for weight loss medications through employer plans requires a direct inquiry. Employer-sponsored plans are not required to disclose their formularies publicly, making it harder to describe coverage patterns with precision. Available data suggests employer plans cover GLP-1 medications at higher rates than ACA Marketplace plans. Large employers have stronger incentives to offer comprehensive benefits. However, many large employer plans have begun restricting or eliminating GLP-1 obesity coverage as costs have grown. A 2025 KFF survey found that even among employers who offer GLP-1 coverage, most apply prior authorization, step therapy requirements, or quantity limits. Step therapy requires a patient to try and fail at least


Female healthcare provider explaining how GLP-1 medications work to a patient during a medical weight loss consultation

How Do GLP-1 Weight Loss Medications Actually Work in the Body?

How Do GLP-1 Weight Loss Medications Actually Work in the Body? Table of Contents 1. Why Understanding the Mechanism Matters 2. The Science Behind How GLP-1 Medications Work 3. What GLP-1 Medications Do to Appetite and the Brain 4. How GLP-1 Medications Affect Blood Sugar and Insulin 5. What Dual GIP and GLP-1 Medications Add to the Picture 6. What to Expect From GLP-1 Treatment in Practice 7. Frequently Asked Questions 8. Why Mechanism Matters for Long-Term Results GLP-1 medications have become the most widely discussed treatment in medical weight loss. Clinical trials show they can produce weight loss of 15 percent or more of body weight, results that were not achievable with previous medications. But most people starting or considering GLP-1 therapy have a straightforward question: exactly how do GLP-1 medications work inside the body? This blog explains the biological mechanism behind GLP-1 medications, what they do to appetite, blood sugar, and metabolism, and why understanding how GLP-1 medications work helps patients use them more effectively. 1. Why Understanding the Mechanism Matters If you have tried to lose weight for years and your hunger keeps winning, you may wonder why. The answer is often hormonal, not a lack of effort. GLP-1 medications target that hormone signal directly. This blog explains how GLP-1 medications work in the body and what that means for your treatment. It covers the effects on appetite, blood sugar, and fat metabolism. It also covers the early effects patients report and the usual timeline for results. GLP-1 receptor agonists are not stimulants, traditional appetite suppressants, or fat blockers. Knowing the mechanism helps you set realistic expectations for side effects and results. If you are comparing two common options, the blog Semaglutide vs. Tirzepatide: Which Is Better for Weight Loss? covers their clinical differences in detail. 2. The Science Behind How GLP-1 Medications Work GLP-1 stands for glucagon-like peptide-1. Cells in the small intestine release this hormone after you eat. It helps control blood sugar, appetite, and digestion. The body breaks it down within minutes, so its natural effect is short. GLP-1 receptor agonists are medications that copy this hormone and bind to its receptors. A receptor is a docking point on a cell that receives a hormone’s signal. These drugs also last much longer in the body. Their half-life, the time the body takes to clear half of a dose, is measured in days rather than minutes. That is why they keep working between doses. According to Cleveland Clinic, GLP-1 agonists mimic the natural hormone and bind to GLP-1 receptors to trigger the same effects. The same source notes that they slow stomach emptying and act on brain areas that process hunger and fullness. Four core actions explain how GLP-1 medications work: Triggering the pancreas to release insulin after food Blocking glucagon, the hormone that raises blood sugar between meals Slowing stomach emptying so food moves more gradually Signaling the brain that the body is full, which lowers appetite Each action adds to weight loss in its own way. 3. What GLP-1 Medications Do to Appetite and the Brain A major part of how GLP-1 medications work is their effect on the brain. GLP-1 receptors sit in the pancreas and gut. They also sit in the hypothalamus and brainstem, the brain regions that govern hunger and the response to food. When the medications activate these receptors, hunger signals drop and fullness arrives sooner. According to NIDDK, GLP-1 medications mimic the natural hormone and target brain areas that regulate appetite and food intake. They lower hunger and raise fullness at the same time. This is one reason they produce greater weight loss than earlier appetite treatments. Slower stomach emptying adds to this effect. Food leaves the stomach more gradually, so glucose enters the blood more slowly. Blood sugar stays steadier, and fullness lasts longer. Many patients say hunger no longer returns between meals as it once did. Patients also often report fewer cravings for sugary and high-calorie foods. This may reflect a lower food reward, which is the pull toward calorie-dense foods for pleasure rather than hunger. 4. How GLP-1 Medications Affect Blood Sugar and Insulin GLP-1 medications affect more than appetite. Their effects on blood sugar and insulin are why doctors first developed them for type 2 diabetes. The weight loss benefit became clear later. According to Mayo Clinic, GLP-1 agonists are an FDA-approved class of medications used in obesity treatment. Some are also approved for diabetes, with weight loss as an added benefit. After a meal, these medications prompt the pancreas to release insulin in proportion to the glucose entering the blood. This is called glucose-dependent insulin secretion. The pancreas responds when blood sugar rises, not when it is already low. That lowers the risk of hypoglycemia, or low blood sugar, compared with older diabetes drugs. They also suppress glucagon. Glucagon is the pancreatic hormone that raises blood sugar between meals. With less glucagon, the liver releases less glucose during fasting, and blood sugar stays in a healthier range. Over time, a better insulin response and lower glucagon improve insulin sensitivity. This matters for patients with insulin resistance, which makes weight loss harder and is common in obesity. 5. What Dual GIP and GLP-1 Medications Add to the Picture Tirzepatide works through two receptors. It activates both the GLP-1 receptor and the GIP receptor. GIP stands for glucose-dependent insulinotropic polypeptide. It is an incretin, which is a gut hormone released after eating that helps regulate insulin. GLP-1 suppresses appetite and slows stomach emptying. GIP adds a separate metabolic effect. GIP receptors are found in fat tissue, and activating them may improve how the body handles fat. This may include less fat stored in organs such as the liver. GIP activation may also ease some of the nausea that GLP-1 causes at higher doses. Trial results reflect this added action. In the STEP-1 trial, adults taking semaglutide lost about 15 percent of body weight over 68 weeks (Wilding et al., New England Journal of Medicine,

Female healthcare provider reviewing insulin resistance and weight loss evaluation results with a male patient during a clinical consultation

How Does Insulin Resistance Make Weight Loss So Much Harder?

How Does Insulin Resistance Make Weight Loss So Much Harder? Table of Contents 1. Why Insulin Resistance Matters for Weight Management 2. What Insulin Resistance and Weight Loss Have in Common 3. Who Develops Insulin Resistance and Why 4. How Insulin Resistance Changes Fat Storage and Metabolism 5. Why Conventional Dieting Often Falls Short 6. What Clinical Evaluation Reveals That Dieting Cannot 7. Frequently Asked Questions 8. Getting to the Root of the Problem If you have been trying to lose weight without success and no one has mentioned insulin resistance, that may be the most important missing piece. Insulin resistance and weight loss are closely connected, and the connection runs in both directions. Insulin resistance makes fat loss harder, and excess body fat makes insulin resistance worse. This blog explains what insulin resistance is, how it disrupts fat burning, and why addressing it is essential before weight loss efforts can produce lasting results. 1. Why Insulin Resistance Matters for Weight Management Most people who struggle with weight loss have been told to eat less and move more. This advice is not wrong, but it fails to account for what is happening in a body that has become resistant to insulin. When insulin resistance is present, the body’s response to food changes in ways that make weight gain more likely and fat loss harder. These are not willpower failures. They are measurable biological changes that require a clinical response. Understanding the lab work that identifies insulin resistance before starting a program is an important first step. The connection between insulin resistance and weight loss outcomes is often first revealed through these results. The blog What Lab Tests Are Done Before Medical Weight Loss Treatment? covers those tests in detail, including why fasting insulin and HbA1c are among the most informative markers a provider will review. 2. What Insulin Resistance and Weight Loss Have in Common Insulin is a hormone produced by the pancreas that enables cells in the muscles, liver, and fat tissue to absorb glucose from the bloodstream. In a healthy metabolic state, insulin acts like a key that unlocks the cell and lets glucose in for energy. According to Cleveland Clinic, insulin resistance happens when cells in the muscles, fat, and liver do not respond to insulin as they should, causing the pancreas to produce more insulin to overcome increasing blood glucose levels. Over time, this results in elevated blood glucose and elevated circulating insulin, a state called hyperinsulinemia. The relationship between insulin resistance and weight loss difficulty begins here. High insulin levels signal the body to store energy as fat rather than burn it. When insulin remains chronically elevated, the body stays in near-constant fat storage mode. This is why people with insulin resistance often report eating very little and still not losing weight. The problem is not caloric intake alone. It is the hormonal environment in which those calories are being processed. 3. Who Develops Insulin Resistance and Why Insulin resistance is far more common than most people realize. A 2021 analysis of national health data found that 40 percent of US adults aged 18 to 44 are insulin resistant, a figure that rises significantly with age. According to NIDDK, factors that increase the likelihood of developing insulin resistance include having overweight or obesity especially around the waist, being age 35 or older, having a family history of diabetes, being physically inactive, and having conditions such as polycystic ovary syndrome or sleep apnea. Several additional factors contribute to its development: Excess visceral fat around internal organs is one of the strongest drivers of insulin resistance A diet high in refined carbohydrates promotes repeated insulin spikes that reduce cellular sensitivity over time Physical inactivity reduces the muscle tissue that absorbs circulating glucose Hormonal changes with aging, declining testosterone in men and declining estrogen in women, impair insulin sensitivity independently of diet Chronic stress elevates cortisol, which directly opposes insulin action Many people develop insulin resistance gradually over years with no obvious symptoms. The pancreas compensates by producing more insulin, keeping blood glucose in a normal range. Someone can have significant insulin resistance without a diabetes diagnosis and without warning signs until weight loss resistance and fatigue begin to appear. 4. How Insulin Resistance Changes Fat Storage and Metabolism Insulin resistance disrupts weight management well beyond simple calorie math. It changes how the body handles energy at the cellular level. According to NIH NCBI StatPearls, the three primary sites of insulin resistance are skeletal muscle, the liver, and adipose tissue. In a state of chronic caloric surplus, these tissues become resistant to insulin signaling, directly changing how glucose is processed and where fat accumulates. Skeletal Muscle Skeletal muscle accounts for up to 70 percent of glucose disposal in a healthy metabolic state. When muscle develops insulin resistance, its ability to absorb glucose drops significantly. Excess glucose is shunted to the liver, where it is converted to fat through a process called de novo lipogenesis. The Liver When the liver receives excess glucose from insulin-resistant muscle, it begins storing that glucose as fat. Liver insulin resistance also impairs the suppression of gluconeogenesis. The liver continues releasing glucose into the bloodstream even when blood sugar is already elevated, compounding the cycle of high glucose and high insulin. Adipose Tissue In insulin-resistant fat tissue, the normal ability of insulin to suppress fat breakdown fails. This raises circulating free fatty acids, which further impairs insulin sensitivity in both muscle and liver, creating a self-reinforcing cycle that makes fat loss progressively harder. 5. Why Conventional Dieting Often Falls Short The insulin resistance and weight loss cycle explains why the body can stop responding even to significant caloric restriction. When insulin levels remain chronically elevated, the body cannot easily switch into fat-burning mode. Standard calorie-restricted diets do not directly lower circulating insulin or improve cellular insulin sensitivity. They reduce caloric input, but the hormonal environment continues to favor fat storage over fat burning. This is why some people lose weight initially and then

Female healthcare provider reviewing clinical information on a tablet with a female patient during a consultation about losing weight after 40

Why Does Losing Weight Get So Much Harder After You Turn 40?

Why Does Losing Weight Get So Much Harder After You Turn 40? Table of Contents 1. It Is Not Just in Your Head 2. The Metabolic Reality of Losing Weight After 40 3. How Hormonal Shifts Drive Weight Gain in Midlife 4. The Role of Muscle Loss in Slowing Metabolism 5. Cortisol, Sleep, and Stress as Hidden Weight Drivers 6. What Changes When You Add Clinical Support 7. Frequently Asked Questions 8. What This Means Going Forward At some point in your 40s, something shifts. The same habits that kept your weight stable in your 30s stop working. You may be eating the same foods, staying active, and still watching the scale climb. If this sounds familiar, losing weight after 40 is genuinely harder, and the reasons are biological, not personal. This blog covers the key biological changes that make losing weight after 40 more difficult and what the clinical evidence says about addressing them. 1. It Is Not Just in Your Head One of the most frustrating things about midlife weight gain is how invisible the causes feel. From the outside, your habits have not changed. From the inside, your body is operating under entirely different metabolic conditions than it was a decade ago. Several distinct biological changes converge in your 40s to make weight management harder: Resting metabolic rate declines as muscle mass decreases with age Hormonal shifts change how the body stores and distributes fat Cortisol sensitivity increases in response to chronic stress Insulin sensitivity decreases, making blood sugar regulation less efficient Sleep disruption becomes more common, amplifying appetite hormones These changes accumulate gradually over years. That is why the shift often feels sudden even though it has been building for some time. For anyone already exploring clinical options, understanding how GLP-1 medications compare is a useful next step. The blog Semaglutide vs. Tirzepatide: Which Is Better for Weight Loss? covers those differences in detail. 2. The Metabolic Reality of Losing Weight After 40 Metabolism is the rate at which the body converts food and stored energy into fuel. A slower metabolism means the body burns fewer calories at rest than it once did. According to NIH News in Health, adults in the United States can expect to gain 10 to 25 pounds between their 20s and 40s. NIH aging expert Dr. Rafael de Cabo explains that metabolism tends to slow with age while appetite does not, producing a steady increase in body weight over time. The reason is structural. The body’s primary calorie-burning tissue is skeletal muscle. As muscle mass declines with age, resting metabolic rate falls with it. A person who weighs the same at 45 as they did at 30 may have significantly less muscle, meaning they need fewer calories and are more likely to store the excess as fat. Losing weight after 40 is harder in part because the caloric equation has changed. The same diet that maintained a stable weight at 32 may produce consistent weight gain at 45, not because of changed habits but because of how the body now processes energy. 3. How Hormonal Shifts Drive Weight Gain in Midlife Hormonal changes in midlife directly affect body composition, fat distribution, and metabolic rate. These changes affect both men and women, though the timing and mechanisms differ. Estrogen Decline in Women According to Mayo Clinic, the hormonal changes of menopause make it more likely for weight gain to occur around the abdomen, and that losing muscle mass with age slows the rate at which the body burns calories. As estrogen declines during perimenopause, fat shifts to the abdominal region. This visceral fat accumulates around internal organs and is associated with elevated inflammation, insulin resistance, and cardiovascular risk. Perimenopause typically begins in the mid-to-late 40s, overlapping with the years when resting metabolic rate is already declining due to muscle loss. Testosterone Decline in Men In men, testosterone declines gradually from the early 30s and accelerates in the mid-40s. Testosterone supports muscle mass, fat metabolism, and insulin sensitivity. As levels fall, the body becomes less efficient at building muscle. Fat accumulates in the abdominal area, resting metabolic rate falls, and insulin resistance can develop or worsen. Men with clinically low testosterone often notice changes in body composition even without lifestyle shifts. 4. The Role of Muscle Loss in Slowing Metabolism Muscle loss with age, known clinically as sarcopenia, is one of the most significant contributors to midlife weight gain. Skeletal muscle burns more calories at rest than fat tissue. As it declines, the body’s baseline caloric expenditure drops and the same habits produce different results. Sarcopenia begins in the mid-30s and accelerates after 40. Research indicates adults lose approximately three to five percent of muscle mass per decade after age 30. Several factors compound this process: Sedentary work reduces the daily movement that supports muscle maintenance Protein needs increase with age even as intake often decreases Sleep disruption impairs overnight growth hormone release, reducing the body’s capacity to repair muscle tissue Hormonal decline in both testosterone and estrogen removes key signals that support muscle retention The relationship between muscle loss and weight gain runs in both directions. Less muscle lowers metabolic rate, making fat gain more likely. Accumulated visceral fat promotes inflammation that further impairs muscle function. 5. Cortisol, Sleep, and Stress as Hidden Weight Drivers Beyond hormonal and metabolic changes, cortisol dysregulation and sleep disruption are two frequently underestimated contributors to midlife weight gain. Cortisol and Abdominal Fat Cortisol is the body’s primary stress hormone, produced in response to perceived stress. When chronically elevated, it promotes abdominal fat storage, increases appetite for calorie-dense foods, and impairs glucose metabolism. Chronic stress is common in midlife. Professional demands, caregiving, and financial pressures keep cortisol elevated for extended periods, creating a consistent hormonal signal that drives visceral fat accumulation regardless of diet. Sleep and Appetite Hormones According to Cleveland Clinic, sleep is essential to regulating hormones, mood, and physical health. Poor sleep raises ghrelin, which signals hunger, and lowers leptin, which signals fullness. The

Healthcare provider reviewing lab tests for weight loss results with a patient

What Lab Tests Are Done Before Medical Weight Loss Treatment?

What Lab Tests Are Done Before Medical Weight Loss Treatment? Table of Contents 1. Why Lab Work Comes Before Treatment 2. The Core Lab Tests for Weight Loss Before Starting 3. Blood Sugar and Insulin Resistance Markers 4. Thyroid Function Testing 5. Hormone Panel Assessment 6. How Lab Results Shape Your Treatment Plan 7. Frequently Asked Questions 8. Understanding the Clinical Picture Before You Begin If you have been thinking about starting a medical weight loss program, one of the first things your provider will do is order blood work. The lab tests for weight loss ordered before treatment are the foundation on which your entire program is built. They tell your provider what is happening inside your body, whether any biological factors are working against your ability to lose weight, and which treatment approach fits your individual health profile. This blog walks through the specific tests typically ordered before starting, what each one measures, and why the results matter for your treatment plan. 1. Why Lab Work Comes Before Treatment Medical weight loss is different from a commercial diet program precisely because it begins with data rather than assumptions. A licensed healthcare provider does not prescribe treatment based on how much weight you want to lose. They prescribe treatment based on what your body’s current metabolic, hormonal, and biochemical state actually reveals. According to NIH — NCBI Bookshelf, laboratory evaluation at the initial obesity-focused visit should include a comprehensive metabolic panel, a complete blood count, thyroid status, and a cardiometabolic risk assessment including a lipid panel and HbA1c. This standard framework ensures that the most important drivers of weight gain and weight loss resistance are identified before any medication is selected. Lab results serve several critical functions before starting: They identify conditions such as insulin resistance, hypothyroidism, or hormonal imbalances that may be actively contributing to weight gain They establish a baseline against which future progress can be measured They determine whether a patient is a good candidate for specific medications, including GLP-1 receptor agonists They flag safety considerations that must be accounted for before starting treatment They help build a personalized program rather than a generic one The lab tests for weight loss ordered before treatment are not an obstacle to starting. They are the reason the treatment is likely to work. The blog What Happens at Your First Medical Weight Loss Consultation? walks through the full first visit process in detail, including how lab work fits into the overall evaluation. 2. The Core Lab Tests for Weight Loss Before Starting The specific panels ordered may vary depending on health history, age, and symptoms. However, a standard pre-treatment evaluation typically includes the following. Comprehensive Metabolic Panel The comprehensive metabolic panel, or CMP, is one of the most widely used lab tests in clinical medicine. According to Cleveland Clinic, a basic metabolic panel provides helpful information about the body’s chemical balance and metabolism, measuring substances including glucose, calcium, electrolytes, and markers of kidney function. The comprehensive version adds liver function tests. In a pre-treatment weight loss evaluation, the CMP informs treatment decisions in several ways: Fasting glucose reveals whether blood sugar is within normal range or suggests prediabetes or diabetes Kidney function markers including creatinine confirm the kidneys are processing waste efficiently before prescribing certain medications Liver function tests including ALT and AST assess whether the liver can safely metabolize weight loss medications Electrolytes confirm fluid and mineral balance before treatment begins Complete Blood Count The complete blood count, or CBC, measures the cellular components of the blood, including red blood cells, white blood cells, and platelets. In a pre-treatment evaluation, the CBC helps identify anemia, which can cause fatigue that mimics or compounds energy issues related to excess weight. It also provides a baseline hematocrit level, which is important to document before starting GLP-1 therapy. Lipid Panel The lipid panel measures cholesterol levels including total cholesterol, LDL, HDL, and triglycerides. Elevated triglycerides and low HDL are markers of metabolic syndrome, which commonly accompanies obesity and insulin resistance. The lipid panel serves as both a safety baseline and a clinical indicator of cardiovascular risk. 3. Blood Sugar and Insulin Resistance Markers Blood sugar regulation is one of the most important areas assessed before starting a medical weight loss program. The lab tests for weight loss that fall into this category provide some of the most clinically useful information. Fasting Blood Glucose Fasting blood glucose is drawn after at least eight hours without eating. It provides a snapshot of blood sugar levels at rest. A result above 100 mg/dL indicates prediabetes. A result above 126 mg/dL on two separate occasions meets the diagnostic threshold for type 2 diabetes. Both findings significantly affect which medications are most appropriate. HbA1c HbA1c reflects average blood sugar levels over the previous two to three months. Unlike fasting glucose, it provides a broader picture of how well blood sugar has been regulated over time. An HbA1c between 5.7 and 6.4 percent indicates prediabetes. A result of 6.5 percent or above confirms type 2 diabetes. These results are particularly relevant for patients who may not yet have a formal diagnosis but are experiencing unexplained fatigue or cravings. Fasting Insulin Some providers include fasting insulin alongside fasting glucose to calculate a measure of insulin resistance. When insulin levels are elevated despite normal glucose, it indicates the pancreas is overworking to maintain blood sugar control. This pattern often appears before a diabetes diagnosis and directly contributes to abdominal fat storage. 4. Thyroid Function Testing Thyroid function is one of the most commonly overlooked contributors to unexplained weight gain. It is a standard component of pre-treatment lab work for medical weight loss. TSH TSH is the primary screening marker for thyroid function. An elevated TSH indicates an underactive thyroid, or hypothyroidism. An underactive thyroid slows metabolism, causes fatigue, and makes losing weight significantly harder even without any other contributing factors. When identified before starting a program, it can be addressed directly so treatment is not working against an

Healthcare provider reviewing keeping weight off after GLP-1 progress with a patient on a laptop

Can You Keep the Weight Off After Stopping GLP-1 Treatment?

Can You Keep the Weight Off After Stopping GLP-1 Treatment? Table of Contents 1. Why This Question Matters More Than Ever 2. What Happens in the Body When GLP-1 Treatment Stops 3. What the Research Says About Keeping Weight Off After GLP-1 Treatment 4. Factors That Influence Long-Term Weight Outcomes 5. The Role of Lifestyle Habits in Sustaining Results 6. What a Structured Transition Plan Looks Like 7. Frequently Asked Questions 8. Building a Foundation That Lasts Beyond Medication GLP-1 medications have changed what is possible in medically supervised weight loss. For many people, they represent the first treatment that has produced meaningful, consistent results after years of unsuccessful attempts. But one of the most common questions that comes up, whether someone is just starting treatment or well into their program, is what happens after. Specifically, keeping weight off after GLP-1 treatment ends is a concern that is both clinically important and practically relevant for anyone relying on these medications as part of a structured weight management program. This blog examines what the clinical evidence says about weight outcomes after stopping GLP-1 treatment, what biological and behavioral factors influence those outcomes, and what a thoughtful transition plan looks like. 1. Why This Question Matters More Than Ever GLP-1 receptor agonists, including semaglutide and tirzepatide, are now among the most widely prescribed medications for weight management. Their ability to reduce appetite, improve insulin sensitivity, and produce meaningful fat loss has made them a central component of medical weight loss programs. But as their use has expanded, so has a legitimate clinical question: are the results they produce sustainable once treatment ends? The answer is not simple, and it is not the same for everyone. What the research consistently shows is that keeping weight off after GLP-1 treatment is achievable, but it requires understanding what those medications were doing in the body and building habits that can carry weight management forward once the medication is no longer present. Understanding how semaglutide and tirzepatide compare in terms of their mechanisms and outcomes provides useful context. The blog Semaglutide vs. Tirzepatide: Which Is Better for Weight Loss? covers those differences in detail. 2. What Happens in the Body When GLP-1 Treatment Stops To understand why weight regain occurs after stopping GLP-1 medications, it helps to understand what those medications were doing while active. GLP-1 receptor agonists work by mimicking a naturally occurring hormone that regulates appetite, slows gastric emptying, and improves how the body processes blood sugar. While on the medication, the body benefits from a sustained artificial elevation of this hormonal signal, which suppresses hunger without requiring active willpower. When the medication is discontinued, that hormonal signal disappears. The body does not automatically maintain the same appetite suppression on its own. Several biological responses tend to follow: Appetite hormones such as ghrelin, which signals hunger, return to pre-treatment levels or higher The fullness effect produced by slowed gastric emptying diminishes Caloric intake often increases as appetite normalizes Metabolic adaptations from weight loss, including a reduced resting metabolic rate, remain in place Insulin sensitivity may begin to decline if dietary habits do not support the gains made during treatment According to NIDDK, patients will likely regain some weight after stopping weight management medication, and developing and maintaining healthy eating habits and increasing physical activity may help limit how much weight is regained or support keeping it off. This biological reality is not unique to GLP-1 medications. It reflects the chronic nature of obesity as a condition and the role that ongoing treatment plays in long-term weight management. 3. What the Research Says About Keeping Weight Off After GLP-1 Treatment The clinical data on post-treatment weight outcomes presents a nuanced picture. Earlier randomized controlled trials produced findings that generated concern. The STEP 1 trial extension found that participants who stopped semaglutide after 68 weeks of treatment regained approximately two thirds of their prior weight loss within one year of discontinuation. However, real-world data tells a more varied and encouraging story. According to Cleveland Clinic, a 2026 analysis of nearly 8,000 patients found that discontinuing semaglutide and tirzepatide did not lead to significant weight regain in clinical practice for many patients. Among those treated specifically for obesity, patients lost an average of 8.4 percent of body weight before stopping and regained only 0.5 percent one year later. The study also found that 45 percent of patients kept losing weight or maintained their results after stopping medication. The researchers noted that many patients who stopped their initial GLP-1 medication restarted it, transitioned to a different obesity treatment, or continued working with healthcare providers through lifestyle modification programs. This ongoing clinical engagement appears to be a significant factor in why real-world outcomes differ from controlled trial settings. The takeaway is that keeping weight off after GLP-1 treatment is not automatic, but it is achievable, particularly for patients who remain engaged with a structured clinical program after discontinuation. 4. Factors That Influence Long-Term Weight Outcomes Not every patient who stops GLP-1 treatment experiences the same outcome. Several individual and clinical factors influence whether results are maintained, partially maintained, or lost over time, and understanding them is key to keeping weight off after GLP-1 ends. Duration of Treatment Patients who remain on GLP-1 medications long enough to build stable habits and reach a sustained lower weight tend to have better post-treatment outcomes. The medication creates conditions that make behavioral change easier. The longer those conditions exist, the more opportunity there is to establish habits that will persist. Lifestyle Changes Made During Treatment GLP-1 medications reduce appetite, but they do not change dietary habits automatically. Patients who actively use reduced appetite to build consistent eating patterns, improve food quality, and increase activity levels tend to maintain more of their results than those who relied on medication effect alone. Reason for Stopping Patients who stop due to cost or insurance limitations often face different outcomes than those who stop because they have reached their treatment goals. Cost-driven discontinuation, which occurs before

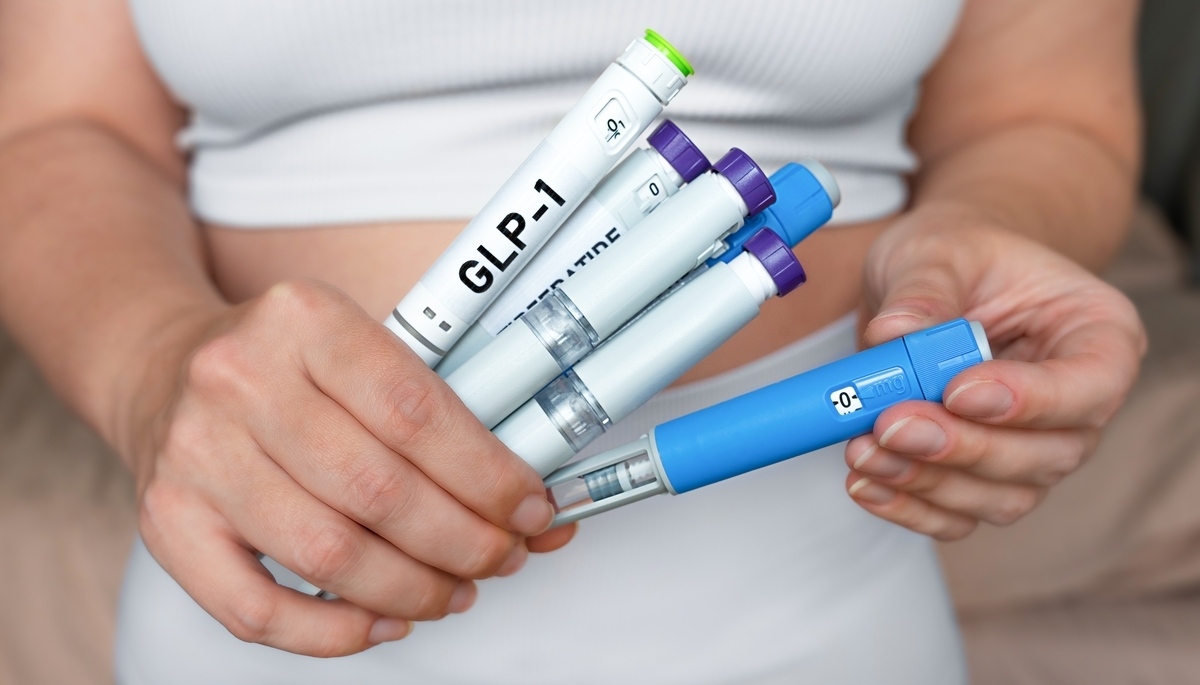
Person holding GLP-1 injection pens comparing semaglutide vs tirzepatide weight loss medication options side by side

Semaglutide vs. Tirzepatide: Which Is Better for Weight Loss?

Semaglutide vs. Tirzepatide: Which Is Better for Weight Loss? Table of Contents 1. What These Two Medications Actually Are 2. How Semaglutide Works for Weight Loss 3. How Tirzepatide Works Differently 4. Semaglutide vs Tirzepatide Weight Loss: What the Clinical Data Shows 5. Side Effects: How the Two Medications Compare 6. Who Tends to Do Better on Each Medication 7. Frequently Asked Questions 8. The Bottom Line Two prescription weight loss medications have changed how clinicians approach obesity treatment over the past several years. Semaglutide and tirzepatide are both injectable medications used in medically supervised programs, and both have produced results that older treatments could not match. If you have been researching options, you have likely come across both names and wondered how they differ. The comparison of semaglutide vs tirzepatide weight loss outcomes is now one of the most discussed topics in obesity medicine, and the clinical evidence gives a clearer picture than most people expect. This article explains how each medication works, what the head-to-head research shows, how their side effect profiles differ, and what factors tend to influence which one may be more appropriate for a given patient. 1. What These Two Medications Actually Are Semaglutide is a glucagon-like peptide-1 (GLP-1) receptor agonist. It mimics a hormone the body naturally produces after eating, one that signals fullness, slows how quickly the stomach empties, and reduces appetite. It is the active ingredient in Wegovy, which is the formulation approved for chronic weight management in adults. Tirzepatide is a dual receptor agonist. It targets both the GLP-1 receptor and a second receptor called the glucose-dependent insulinotropic polypeptide (GIP) receptor. Tirzepatide is the active ingredient in Zepbound, the formulation approved for weight management. The dual mechanism is the key distinction between the two medications, and it is the reason their outcomes differ in clinical trials. Both are administered as once-weekly subcutaneous injections. Both require a prescription and are used as part of a broader medically supervised program that includes dietary guidance and monitoring. 2. How Semaglutide Works for Weight Loss Semaglutide reduces body weight primarily by suppressing appetite and slowing gastric emptying. When GLP-1 receptors are activated, the brain receives signals that the body is full, which reduces overall caloric intake. Patients on semaglutide typically report a significant reduction in hunger and a lower interest in food, particularly calorie-dense foods. According to a network meta-analysis published in PMC, semaglutide at its approved 2.4 mg dose consistently produced meaningful weight reduction across multiple randomized controlled trials in non-diabetic adults with obesity. The STEP trials, which are the major clinical studies behind semaglutide’s approval, showed an average weight loss of approximately 15 percent of body weight over 68 weeks. Understanding how semaglutide performs on its own is an important part of evaluating the semaglutide vs tirzepatide weight loss question with an accurate baseline. Semaglutide also improves insulin sensitivity and blood sugar regulation, which are factors that independently affect how the body stores and metabolizes fat. These metabolic benefits contribute to weight loss beyond appetite suppression alone. 3. How Tirzepatide Works Differently Tirzepatide activates both the GLP-1 and GIP receptors simultaneously. The GIP receptor plays a role in fat metabolism, energy balance, and how the body responds to insulin in fat tissue. Activating both pathways together appears to produce additive effects on appetite regulation and metabolic function that exceed what GLP-1 activation alone achieves. The GIP component also appears to reduce some of the gastrointestinal side effects associated with GLP-1 medications, which is one reason tirzepatide tends to have a different tolerability profile compared to semaglutide. According to the FDA’s guidance on GLP-1 medications used for weight loss, both semaglutide and tirzepatide are FDA-approved medications for weight management, and patients should only use them under the supervision of a licensed healthcare provider using the approved formulations. The FDA has raised specific concerns about unapproved compounded versions of both drugs, noting that these have not been reviewed for safety or effectiveness. 4. Semaglutide vs Tirzepatide Weight Loss: What the Clinical Data Shows The most significant development in the comparison of semaglutide vs tirzepatide weight loss outcomes came from the SURMOUNT-5 trial, the first head-to-head clinical study to directly compare the two medications in adults with obesity but without type 2 diabetes. The results were notable: Tirzepatide produced an average weight loss of 20.2 percent of body weight over 72 weeks Semaglutide produced an average weight loss of 13.7 percent of body weight over the same period Participants on tirzepatide were roughly twice as likely to achieve at least 25 percent body weight reduction compared to those on semaglutide Tirzepatide also produced greater reductions in waist circumference across the trial period The same meta-analysis from PMC noted above, which reviewed multiple randomized controlled trials across varying doses, confirmed that tirzepatide demonstrated superiority over semaglutide in percentage weight reduction, with a mean difference of approximately 6.1 percent greater weight loss favoring tirzepatide. These numbers represent population-level averages. Individual outcomes vary based on starting weight, metabolic health, adherence, diet, and other factors. 5. Side Effects: How the Two Medications Compare Both medications share a similar class of side effects because they both activate GLP-1 receptors. The most commonly reported effects include: Nausea, particularly during dose escalation Constipation or diarrhea Vomiting in some patients Abdominal discomfort Reduced appetite, which can occasionally feel pronounced in early weeks The difference between the two lies in the frequency and pattern of these effects. Semaglutide tends to produce more nausea as the dominant side effect. Tirzepatide, with its GIP component, tends to produce less nausea overall but may cause more diarrhea in some patients. According to the FDA press announcement on semaglutide’s cardiovascular approval, semaglutide has demonstrated cardiovascular benefits in adults with obesity and established cardiovascular disease, a clinical consideration that extends beyond weight loss alone. Both medications carry a boxed warning regarding a potential risk of thyroid C-cell tumors observed in animal studies. Patients with a personal or family history of medullary thyroid carcinoma or Multiple Endocrine Neoplasia syndrome type

Doctor reviewing health records with a male patient during a medical weight loss candidate evaluation at a clinic

Who Is a Good Candidate for Medical Weight Loss Treatments?

Who Is a Good Candidate for Medical Weight Loss Treatments? Table of Contents 1. Medical Weight Loss Is Not for Everyone and Here Is Who It Is Designed For 2. The BMI Numbers Providers Actually Use 3. Why a Single Number Does Not Capture the Full Clinical Picture 4. Medical Conditions That Make Someone a Stronger Medical Weight Loss Candidate 5. Factors That May Affect Which Treatment Is Appropriate 6. Inside the Candidacy Evaluation 7. Frequently Asked Questions 8. Putting It All Together You have tried adjusting your diet. You have increased your activity level. You have followed programs that worked for others but did not seem to work for you. If this sounds familiar, you may have started wondering whether a structured medical approach could offer something different. Knowing whether you are a medical weight loss candidate is a practical first step before investing time and energy into a new program. The answer depends on more than just how much weight you want to lose. It involves a clinical picture that includes your BMI, your health history, existing medical conditions, and how your body has responded to previous efforts. This article explains the criteria providers use to determine candidacy, what conditions strengthen a case for medical treatment, and what the evaluation process typically involves. 1. Medical Weight Loss Is Not for Everyone and Here Is Who It Is Designed For Medical weight loss is a clinically supervised approach designed for people whose weight presents real health risks and who have not achieved sufficient results through lifestyle changes alone. It is not a program intended for someone who wants to lose a few pounds before an event. Understanding whether you qualify matters for several reasons: It helps set realistic expectations about what the program can and cannot do It ensures that treatment is matched to the appropriate level of clinical need It reduces the risk of using prescription medications in situations where they are not indicated It helps providers identify underlying conditions that may be driving weight gain in the first place The clinical criteria for candidacy are well established in medical guidelines and are applied consistently across supervised programs. 2. The BMI Numbers Providers Actually Use Body mass index is the primary screening tool used to assess whether someone is a medical weight loss candidate. While BMI has limitations as a standalone measure, it provides a standardized starting point that providers use alongside other clinical information. According to StatPearls, published by the NIH, the established BMI thresholds for pharmacologic weight loss treatment are: BMI of 30 or higher with no additional weight-related health conditions BMI of 27 or higher when at least one weight-related comorbidity is present, such as type 2 diabetes, high blood pressure, or high cholesterol These thresholds reflect the point at which excess body weight begins to present measurable health risks that can be meaningfully addressed through medically supervised intervention. A person with a BMI below these thresholds may benefit from lifestyle counseling but would not typically qualify for prescription-based medical weight loss treatment. BMI is calculated using height and weight. A BMI between 18.5 and 24.9 is considered healthy. A BMI between 25 and 29.9 is classified as overweight. A BMI of 30 or above is classified as obese, and a BMI of 40 or above is classified as severely obese. Providers use these categories as a starting point, but the full picture of what gets reviewed before treatment is recommended goes well beyond a single number. The blog What Happens at Your First Medical Weight Loss Consultation? explains exactly how providers use BMI alongside other clinical findings during that initial visit. 3. Why a Single Number Does Not Capture the Full Clinical Picture BMI is a useful screening tool, but it does not capture everything that matters when evaluating a medical weight loss candidate. Two people with identical BMIs can have very different metabolic profiles, body compositions, and health risks. According to a guideline-directed review published in PMC, clinical guidelines now recognize that eligibility for anti-obesity medications should consider not only BMI but also the presence of comorbidities, prior treatment history, and individual patient characteristics. Some guidelines have also introduced ethnicity-specific BMI thresholds because the relationship between body weight and metabolic risk varies across populations. Providers evaluating candidacy will typically look beyond the number on the scale and consider: Where body fat is distributed, particularly whether excess fat is concentrated in the abdominal region Markers of metabolic health including blood sugar, insulin sensitivity, cholesterol, and blood pressure How the body has responded to previous weight loss attempts Whether hormonal factors such as thyroid function or sex hormone levels are contributing to weight management difficulties The presence of conditions like insulin resistance or metabolic syndrome that increase cardiovascular and metabolic risk This broader picture allows providers to identify the right level of intervention for each individual rather than applying a single threshold rigidly. 4. Medical Conditions That Make Someone a Stronger Medical Weight Loss Candidate Certain health conditions not only increase the likelihood that someone will qualify for medical weight loss treatment but also increase the urgency of addressing body weight as a clinical priority. According to the CDC’s Adult Obesity Facts, approximately 58 percent of adults with obesity have high blood pressure, and around 23 percent have diabetes. These comorbidities are directly influenced by body weight and can improve meaningfully with clinically supervised weight loss. Conditions that typically strengthen candidacy include: Type 2 diabetes or prediabetes. Excess body weight worsens insulin resistance. Weight loss of even 5 to 10 percent of body weight can produce measurable improvements in blood sugar control. High blood pressure. Carrying excess weight increases the workload on the cardiovascular system. Reducing body weight is one of the most effective non-pharmaceutical interventions for lowering blood pressure. High cholesterol or dyslipidemia. Obesity is closely associated with elevated triglycerides and reduced HDL cholesterol. Weight loss can improve lipid panels without medication changes in some patients. Obstructive sleep apnea. Excess weight, particularly around

Male provider discussing low testosterone and weight gain with a patient in a clinic

Does Low Testosterone Make It Significantly Harder to Lose Weight?

Does Low Testosterone Make It Significantly Harder to Lose Weight? Table of Contents 1. The Connection Between Testosterone and Body Weight 2. How Low Testosterone and Weight Gain Are Linked 3. The Hypogonadal-Obesity Cycle Explained 4. Other Ways Low Testosterone Affects Weight Loss Efforts 5. How Low Testosterone Is Diagnosed 6. What Addressing Low Testosterone Can Mean for Weight Management 7. Frequently Asked Questions 8. Understanding the Full Picture Unexplained weight gain is one of the most common frustrations men bring to a healthcare provider. Diet changes produce limited results. Exercise does not seem to shift the scale. Energy is low, motivation is inconsistent, and body composition shifts in ways that feel difficult to control. One factor that often goes unexamined in these situations is hormone levels, specifically testosterone. The relationship between low testosterone and weight gain is well established in clinical research, and understanding how these two conditions interact is an important part of addressing weight loss resistance in men. This blog explains the biological mechanisms that connect testosterone to body composition, why low testosterone can make losing weight significantly harder, and what the clinical evidence says about addressing both issues together. 1. The Connection Between Testosterone and Body Weight Testosterone is the primary male sex hormone, but its role extends far beyond reproduction. It plays a direct role in regulating metabolism, muscle mass, fat distribution, and energy balance. When testosterone levels are adequate, the body maintains a composition that favors lean muscle over fat storage. When levels decline, that balance shifts. According to Mayo Clinic, low testosterone, also known as male hypogonadism, can cause increased body fat, reduced muscle bulk and strength, decreased energy, and changes in mood. These are not isolated symptoms. They are interconnected metabolic effects that compound over time. Testosterone influences body weight through several biological pathways: It promotes the development and maintenance of skeletal muscle, which burns more calories at rest than fat tissue It regulates how fat cells develop and where fat is stored in the body It supports insulin sensitivity, which affects how efficiently the body processes glucose and stores energy It influences energy levels and motivation, which affect how consistently a person can maintain physical activity When any of these pathways are disrupted by declining testosterone levels, weight management becomes measurably more difficult even without any change in diet or exercise habits. 2. How Low Testosterone and Weight Gain Are Linked The clinical evidence connecting low testosterone and weight gain is consistent and well documented. Research published in Obesity Reviews found that low testosterone levels are associated with increased fat mass, particularly central adiposity, and reduced lean mass in males. The study also noted that testosterone deficiency is associated with impaired glucose control, reduced insulin sensitivity, and dyslipidemia. According to PubMed, testosterone is a key hormone in the pathology of metabolic diseases such as obesity, and a bidirectional relationship between testosterone and obesity exists, meaning each condition can worsen the other. In practical terms, this means a man with low testosterone is likely to experience: Gradual accumulation of abdominal fat even without significant dietary changes Reduced muscle mass, which lowers the resting metabolic rate and reduces overall calorie expenditure Increased fatigue and reduced motivation, which affects adherence to exercise and healthy eating Greater insulin resistance, which promotes fat storage and makes weight loss harder to achieve through diet alone Changes in appetite regulation that may increase cravings for calorie-dense foods These effects do not occur in isolation. They reinforce each other, making the overall metabolic environment progressively less favorable for weight loss over time. 3. The Hypogonadal-Obesity Cycle Explained One of the most clinically significant aspects of the relationship between low testosterone and weight gain is that the two conditions create a self-reinforcing cycle. Understanding this cycle helps explain why some men find it nearly impossible to lose weight through conventional methods alone. The cycle works as follows: Low testosterone leads to increased fat mass, particularly in the abdominal region. Abdominal fat contains an enzyme called aromatase, which converts testosterone into estrogen. The more abdominal fat present, the more testosterone is converted, further reducing testosterone levels. Lower testosterone leads to further muscle loss and fat gain, which increases aromatase activity and drives testosterone even lower. The declining testosterone also worsens insulin resistance, which promotes additional fat storage and makes it harder for the body to use stored fat as energy. This cycle, sometimes called the hypogonadal-obesity cycle, is one of the reasons why addressing low testosterone and weight gain together tends to produce better outcomes than focusing on either issue in isolation. Treating the weight without addressing the hormonal component leaves a significant biological driver of weight gain unaddressed. 4. Other Ways Low Testosterone Affects Weight Loss Efforts Beyond the direct metabolic effects, low testosterone creates several indirect barriers to effective weight loss that are worth understanding. Reduced Muscle Protein Synthesis Testosterone stimulates muscle protein synthesis, which is the process by which the body builds and repairs muscle tissue. When testosterone is low, this process slows down. Men with low testosterone may find that even with consistent resistance training, they make slower progress building or maintaining muscle. Since muscle tissue burns more calories at rest than fat tissue, less muscle means a lower baseline metabolic rate. Sleep Disruption Low testosterone is associated with disrupted sleep, including increased rates of sleep apnea. Poor sleep quality independently raises cortisol levels, promotes fat storage, and impairs appetite regulation. A man who is not sleeping well due to low testosterone faces a compounding set of hormonal disruptions that collectively make weight management harder. Mood and Motivation Testosterone plays a role in mood regulation, motivation, and cognitive drive. Men with low testosterone often report feeling less motivated to exercise, less focused, and more prone to low mood. These psychological effects directly affect the behavioral consistency that weight loss requires. Cortisol Imbalance Low testosterone is often accompanied by a relative increase in cortisol, the body’s primary stress hormone. Elevated cortisol promotes abdominal fat storage, increases appetite,

Healthcare provider explaining a medical weight loss consultation to a female patient in a modern clinic

What Happens at Your First Medical Weight Loss Consultation?

What Happens at Your First Medical Weight Loss Consultation? Table of Contents 1. What Is a Medical Weight Loss Consultation 2. Who Should Consider a Medical Weight Loss Consultation 3. What to Expect During Your First Visit 4. Lab Work and Health Assessments 5. How Your Treatment Plan Gets Built 6. What Happens After the Consultation 7. Frequently Asked Questions 8. Making an Informed Decision About Medical Weight Loss If you have been thinking about starting a structured weight loss program but are not sure what to expect, you are not alone. Many people put off scheduling their first medical weight loss consultation simply because they do not know what the appointment involves. Understanding what happens from the moment you walk in can make the process feel far less uncertain and help you arrive prepared. This blog walks through each stage of a first medical weight loss consultation, from the initial health review to the creation of a personalized treatment plan, so you know exactly what to expect before you book your appointment. 1. What Is a Medical Weight Loss Consultation Before getting into what happens during the visit, it helps to understand what a medical weight loss consultation is and how it differs from a routine check-up or a commercial diet program. A medical weight loss consultation is an in-depth clinical appointment conducted by a licensed healthcare provider, typically a physician or nurse practitioner, whose focus is on identifying the underlying biological, hormonal, and metabolic factors contributing to weight gain. Unlike general wellness visits, the consultation is specifically structured around building a personalized weight management strategy based on your individual health data. According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), a well-structured weight loss program should begin with a health professional reviewing your medical history, measuring key health indicators, and assessing any medications or conditions that may be affecting your weight. This is exactly what a structured consultation is designed to do. At Elevate Testosterone and Weight Loss in Oswego, IL, the consultation is a clinical evaluation. Your provider reviews your health history, orders lab work, and uses real data to determine what approach is right for your body. 2. Who Should Consider a Medical Weight Loss Consultation A medical weight loss consultation is appropriate for a wide range of individuals. You do not need to meet a specific weight threshold or have a diagnosed condition to benefit from a structured clinical approach. The consultation is typically a strong fit for people who: Have struggled to lose weight despite consistent diet and exercise efforts Have experienced unexplained weight gain, especially in the abdominal area Suspect that hormonal changes or metabolic slowdown may be contributing to weight gain Have been told by a healthcare provider that their weight is affecting other health markers Have tried multiple programs or diets without achieving lasting results Want a medically guided approach rather than a self-directed one Weight management is influenced by far more than calories in and calories out. Factors such as insulin resistance, thyroid function, sleep quality, cortisol levels, and hormonal changes all play a significant role in how the body stores and uses energy. A medical weight loss consultation is the appropriate starting point for anyone whose weight struggles have a biological component that a standard diet program is not equipped to address. 3. What to Expect During Your First Medical Weight Loss Consultation The first medical weight loss consultation typically runs between 45 and 60 minutes. The appointment is structured to give your provider a complete picture of your health before any treatment decisions are made. According to Cleveland Clinic, at a first medical weight management visit, the provider conducts a physical exam, reviews personal and family medical history, measures blood pressure and heart rate, and orders blood tests to check blood sugar, cholesterol, and organ function. This is the standard framework most structured programs follow. A first visit generally covers the following: Health History Review Your provider will ask about your current health concerns, past medical diagnoses, medications and supplements you are taking, and any previous weight loss attempts. This includes information about what approaches you have tried, what worked for a period, and why those approaches stopped producing results. Weight and Body Composition Assessment Your provider will record your current weight, calculate your body mass index, and assess body composition where relevant. These baseline measurements are used to track progress throughout the program and to determine the most appropriate starting point for treatment. Lifestyle and Symptom Discussion The consultation also covers your daily habits, including your sleep patterns, stress levels, activity level, and typical eating patterns. These factors directly affect metabolism and hormone balance and are important inputs for building a realistic treatment plan. Your provider may ask about: Energy levels throughout the day Sleep quality and duration Stress levels and how you manage them Meal timing and general eating patterns Level and consistency of physical activity Any symptoms that may suggest hormonal imbalance, such as fatigue, mood changes, or difficulty maintaining muscle Goal Setting Your provider will ask about your weight loss goals and what outcomes matter most to you. Whether your focus is on reducing a specific health risk, improving energy, or achieving a sustainable weight, this conversation shapes the direction of your treatment plan. 4. Lab Work and Health Assessments Lab work is one of the most important components of a medical weight loss consultation and one of the key differences between a clinically supervised program and a self-directed diet. Blood tests allow your provider to identify biological factors that may be working against your weight loss efforts and that would otherwise go undetected. These results guide treatment decisions and ensure the plan is built on accurate health data rather than assumptions. Typical lab panels ordered at or following a first consultation may include: Fasting blood glucose and HbA1c to assess insulin sensitivity and blood sugar regulation Lipid panel to evaluate cholesterol levels Thyroid function tests to rule out